
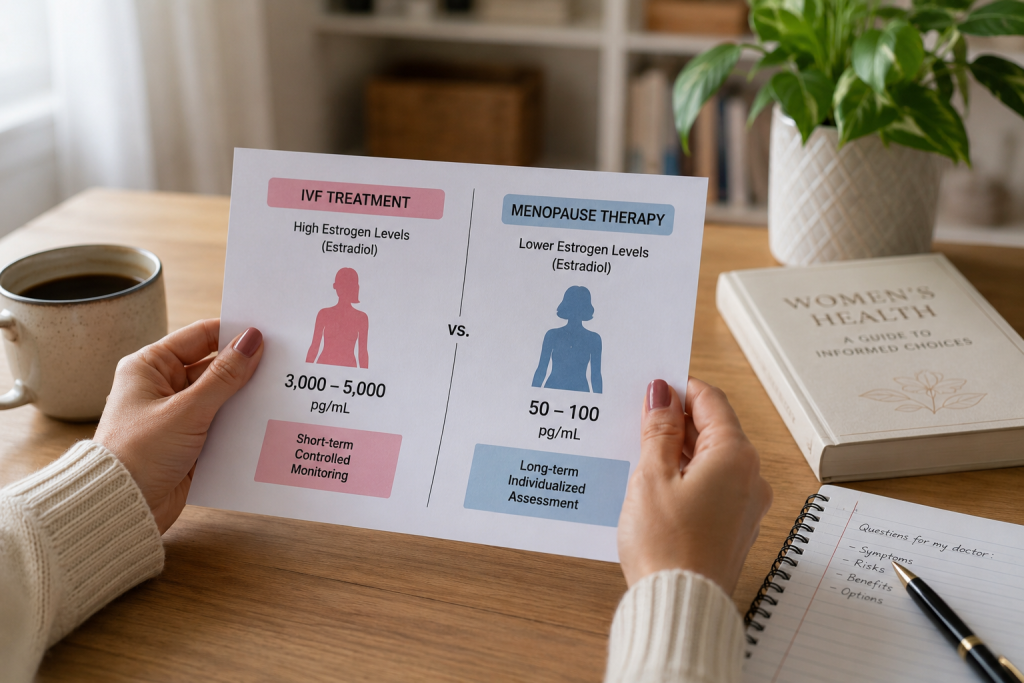
Every so often, a simple graphic makes the rounds on social media and sparks the same heated debate.
On one side is a woman undergoing in vitro fertilization (IVF). The accompanying text explains that her estradiol levels may rise to 3,000, 4,000, or even 5,000 pg/mL during treatment.
On the other side is a woman experiencing menopause who uses hormone therapy to maintain estrogen levels that are only a fraction of those values.
The question underneath is usually straightforward:
If medicine accepts extremely high estrogen levels during IVF, why has hormone therapy after menopause remained so controversial?
At first glance, it sounds like a compelling argument. If the same hormone is involved in both situations, why is it viewed so differently?
The answer, however, reveals one of the most fascinating stories in modern medicine—a story involving scientific breakthroughs, changing assumptions, media headlines, large-scale clinical trials, and decades of ongoing research.
To understand it, we need to go back nearly a century.
Before Menopause Became a Medical Discussion
For most of human history, menopause was viewed as a natural transition rather than a condition that required treatment.
Women described hot flashes, night sweats, sleep disturbances, mood changes, and other symptoms, but medicine had few explanations and even fewer solutions.
Life expectancy played a role as well.
In the early 1900s, many women did not spend decades living beyond menopause. As life expectancy increased throughout the twentieth century, that reality changed dramatically.
Today, women in many developed countries routinely live into their eighties. As a result, a significant portion of life is now spent after reproductive years have ended.
This demographic shift raised an important question.
If women were going to spend 30 or even 40 years after menopause, should symptoms and long-term health changes associated with declining estrogen simply be accepted, or could they be managed more effectively?
The Discovery That Changed Women’s Health
During the 1920s and 1930s, scientists successfully identified and isolated the primary estrogens produced by the human body.
The discovery transformed endocrinology.
Researchers quickly learned that estrogen was not simply a reproductive hormone.
Its influence extended far beyond fertility and pregnancy.
Estrogen receptors were eventually found in bone tissue, blood vessels, skin, the urinary tract, and multiple regions of the brain. This helped explain why hormonal changes could affect so many aspects of health and well-being.
As knowledge expanded, menopause began to be viewed through a broader medical lens.
When Hormone Therapy Was Seen as a Major Medical Breakthrough
By the 1960s, 1970s, and 1980s, hormone therapy had become increasingly common.
For many women, the benefits seemed significant.
Hot flashes became less frequent.
Night sweats improved.
Sleep quality often increased.
Daily life became more manageable.
Researchers also observed that declining estrogen levels contributed to accelerated bone loss after menopause.
This was particularly important because osteoporosis remains one of the leading causes of fractures in older women. In fact, roughly one in two women over age 50 will experience an osteoporosis-related fracture during their lifetime.
Against this backdrop, hormone therapy appeared to offer meaningful advantages.
Some researchers even speculated that it might help protect the cardiovascular system.
By the late 1990s, hormone therapy had become one of the most widely prescribed treatments for menopausal women in the United States, with an estimated 15 million users.
Few anticipated how dramatically the conversation would soon change.
The Study That Changed Everything
In 1991, researchers launched one of the largest women’s health research programs ever conducted: the Women’s Health Initiative, commonly known as WHI.
The hormone therapy arm of the study enrolled more than 16,000 postmenopausal women.
The goal was straightforward but critically important.
Researchers wanted to determine whether the long-term benefits of hormone therapy outweighed its risks.
Participants received either a specific combination of conjugated estrogens and medroxyprogesterone acetate or a placebo.
The findings would have a profound impact on women’s healthcare worldwide.
The Headlines That Reshaped Public Opinion
In July 2002, early WHI results were released.
The media response was immediate.
Headlines appeared across newspapers, television broadcasts, and websites around the world.
Many focused on one message:
“Hormones increase cancer risk.”
“Hormone therapy is dangerous.”
“Women should stop treatment.”
While the study did identify certain increased risks, the public discussion often became far simpler than the actual findings.
The impact was enormous.
Within just a few years, hormone therapy use dropped by more than 50% in many regions.
Millions of women discontinued treatment.
Many physicians altered prescribing practices almost overnight.
Few medical studies have influenced public behavior so rapidly.
What Many People Missed
One of the most important lessons from the WHI controversy involves a concept that often gets lost in public discussions: the difference between relative risk and absolute risk.
Relative risk can sound dramatic.
Absolute risk tells us how many additional cases actually occur within a large population.
For example, some of the WHI findings translated into relatively small increases in absolute numbers when measured across 10,000 women per year.
The risks identified by the study were real, but understanding their scale required careful interpretation.
This nuance was frequently overshadowed by alarming headlines.
As a result, many people came away with the impression that hormone therapy was universally dangerous, a conclusion that was more simplistic than the data itself.
A Second Look at the Evidence
As researchers continued analyzing the results, they noticed something important.
The average participant in the WHI hormone trial was about 63 years old.
Many women had begun treatment more than a decade after menopause.
This raised a new question:
Could timing matter?
Researchers began exploring what later became known as the “timing hypothesis” or “window of opportunity.”
The idea suggested that women who start hormone therapy closer to the onset of menopause may experience a different balance of risks and benefits than women who begin treatment much later.
While research continues, this concept has significantly influenced modern medical guidelines.
Meanwhile, IVF Was Transforming Reproductive Medicine
While debates about menopause intensified, another field of medicine was advancing rapidly.
In 1978, the birth of Louise Brown, the world’s first IVF baby, marked a historic milestone.
At the time, the achievement seemed extraordinary.
Today, assisted reproductive technologies have helped millions of families worldwide.
A key component of IVF is controlled ovarian stimulation.
Under normal circumstances, a single follicle typically matures during each menstrual cycle.
During IVF, physicians aim to stimulate multiple follicles at the same time in order to retrieve several mature eggs.
Each growing follicle produces estradiol.
As more follicles develop, estrogen levels rise accordingly.
This is why estradiol concentrations can reach several thousand pg/mL during certain IVF cycles.
Why High Estrogen Levels in IVF Are Viewed Differently
This is where the social media comparison begins to oversimplify the issue.
Medicine does not evaluate risk based solely on a hormone level.
Context matters.
Age matters.
Treatment goals matter.
Duration of exposure matters.
Monitoring matters.
In IVF, elevated estrogen levels occur for a limited period under close medical supervision.
Blood tests and ultrasound examinations are performed frequently.
Physicians actively monitor patients because excessively high responses can signal complications such as ovarian hyperstimulation syndrome.
In other words, high estrogen levels during IVF are not considered risk-free.
They are accepted because they occur within a carefully controlled clinical setting and serve a specific reproductive purpose.
Are Today’s Hormone Therapies the Same as Those Studied in 2002?
Not necessarily.
This is another detail that is often missing from online discussions.
The WHI evaluated a specific hormone regimen using particular formulations available at that time.
Since then, hormone therapy has evolved.
Different doses, delivery methods, and formulations are now available.
Options may include bioidentical estradiol, micronized progesterone, transdermal patches, gels, and other approaches.
These developments do not eliminate risk, but they illustrate why modern discussions about hormone therapy are more nuanced than simple statements that hormones are either “good” or “bad.”
What Current Medical Organizations Say
More than two decades after the WHI findings, major menopause organizations around the world have adopted a more individualized approach.
Current guidelines generally recognize hormone therapy as the most effective treatment for moderate to severe vasomotor symptoms such as hot flashes and night sweats.
At the same time, experts emphasize that treatment decisions should be personalized.
Not every woman needs hormone therapy.
Not every woman is an ideal candidate.
The decision should consider medical history, symptom severity, age, personal risk factors, and individual preferences.
The Bigger Lesson Behind the Debate
Perhaps the most interesting aspect of this entire discussion is that it is not really about hormones alone.
It is about how science evolves.
It is about how large clinical studies can reshape medical practice.
It is about how media coverage influences public perception.
And it is about how difficult it is to compress decades of research into a single viral image.
The graphic that continues to circulate online does highlight a real question.
But it captures only a small part of a much larger story.
The history of estrogen is not the story of a hormone that is either safe or dangerous.
It is the story of how medicine continually reexamines its assumptions, refines its recommendations, and adapts as new evidence emerges.
And that may be the most important lesson of all: in healthcare, numbers matter, but context often matters just as much.