
For much of his early childhood, Matthew Johnson’s life revolved around illness.
There were medical appointments, medications and specialist equipment. He used mobility aids and a wheelchair. He was fed through a tube. To doctors, charities and members of the public who heard his story, he appeared to be a child living with an extraordinary combination of serious health problems.
His mother, Lisa Hayden-Johnson, was seen as the devoted parent caring for him through it all.
But the medical story surrounding Matthew gradually began to unravel.
Investigators eventually concluded that many of the conditions attributed to him had been fabricated or exaggerated. By the time authorities intervened, a child who was far healthier than people had been led to believe had already spent years living as a severely disabled patient.
Lisa Hayden-Johnson was eventually convicted of child cruelty and perverting the course of justice. In January 2010, she was sentenced to three years and three months in prison.
More than 15 years later, the case has returned to public attention for a very different reason.
Matthew is no longer the little boy whose story was told by adults.
At 25, he is telling it himself.
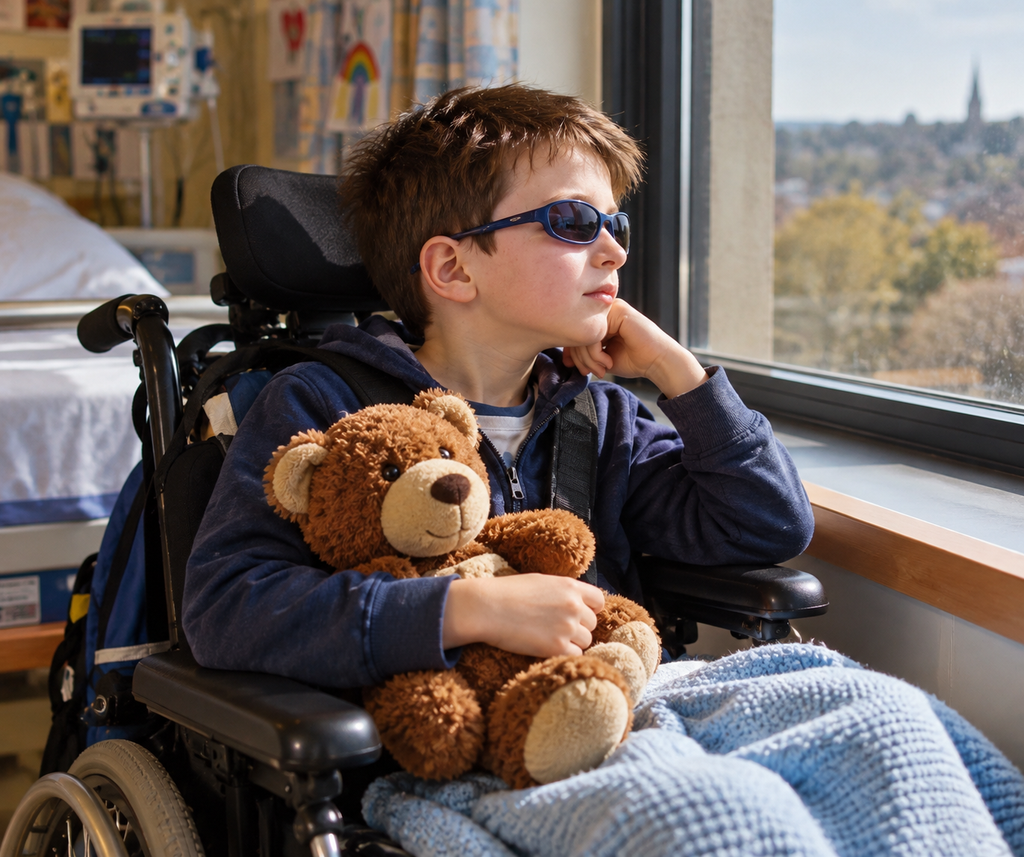
A premature baby whose medical history became increasingly complicated
Matthew was born prematurely in 2001.
Premature babies can genuinely require additional medical care, and Matthew did have health concerns early in life. What followed, however, went far beyond those initial problems.
Over the years, his mother reported an expanding range of serious conditions and symptoms.
Matthew was presented as suffering from illnesses and disabilities including cerebral palsy, cystic fibrosis, diabetes, severe food intolerances and significant difficulties with eating and mobility.
His supposed medical needs increasingly shaped everyday life.
He used mobility equipment and a wheelchair. His feeding became medicalised. At one stage, a gastrostomy tube was inserted so nutrition could be delivered directly into his stomach.
There were also claims that exposure to sunlight posed a danger to him, leading to the use of special glasses.
To someone encountering the family, there was little reason to assume the story was false. Matthew appeared to be surrounded by exactly the equipment one might expect to find around a seriously ill child.
Yet the picture created around him was becoming increasingly disconnected from his actual health.
The numbers reveal how deeply medicine had entered his childhood
Reports from the criminal case described approximately 325 episodes of medical care during Matthew’s childhood.
That figure is sometimes distorted online, so an important distinction is necessary: it does not mean Matthew underwent 325 operations.
The number encompassed medical appointments, assessments, investigations and treatments.
But some of the interventions were unquestionably invasive.
Matthew underwent procedures under general anaesthesia and had operations, including the insertion of a feeding tube.
This is where fabricated illness becomes particularly disturbing.
A false symptom can lead to a real blood test.
A fabricated feeding problem can lead to a real tube being inserted.
An invented disease can result in genuine medication, anaesthesia, hospital admissions and physical risk.
The original illness may not exist, but the consequences of treating it certainly do.
Outside the medical setting, another Matthew sometimes appeared
As concerns grew, evidence emerged that was difficult to reconcile with the medical picture presented by his mother.
Matthew had supposedly been unable to tolerate normal solid food. Yet photographs showed him eating ordinary meals.
He had been portrayed as having serious mobility difficulties, while other images showed him running during a holiday.
People had also seen him doing things that seemed inconsistent with the severe restrictions described to doctors.
None of these observations, taken alone, would prove abuse. Medical conditions can fluctuate, children can have good and bad days, and photographs capture only a moment.
The problem was the accumulating pattern.
The discrepancy between the child described to medical professionals and the child observed elsewhere became increasingly difficult to explain.
Investigators also uncovered evidence that went beyond exaggerating symptoms.
Information reported about the case indicated that medical evidence itself had been manipulated to create the appearance of illness.
At that point, the issue was no longer simply whether an anxious parent had misunderstood her child’s health.
It was about the deliberate creation of a false medical reality.
How can something like this remain undetected?
Matthew’s story produces an understandable reaction: surely doctors should have realised sooner.
The reality is more complicated.
Paediatric medicine depends heavily on information supplied by parents and caregivers.
A toddler cannot provide a detailed medical history. Even older children may struggle to describe symptoms accurately. Some conditions appear intermittently and disappear before a doctor can observe them.
A child may vomit at home but appear perfectly well during an appointment. A seizure-like episode may happen only occasionally. An allergic reaction may be over by the time the child reaches hospital.
Doctors therefore have to listen carefully to caregivers.
Most of the time, that trust is not a weakness. It is an essential part of treating children.
Fabricated or induced illness exploits that relationship.
The UK’s National Health Service notes that these cases can be particularly difficult to recognise because healthcare professionals normally assume that parents are acting in their child’s best interests. At the same time, clinicians must avoid the opposite mistake: dismissing a genuine but difficult-to-diagnose illness as fabrication.
That distinction matters enormously.
A child having unexplained symptoms does not mean a parent is lying.
Repeated medical appointments do not prove abuse.
Normal test results do not prove abuse either.
Concern generally develops from a broader pattern of inconsistencies between reported symptoms, clinical findings and independently observed behaviour.
At six years old, Matthew’s life changed
Eventually, concerns about Matthew’s medical history led to intervention.
In 2007, when he was six, he was removed from his mother’s care.
For most children, leaving hospital equipment behind might sound like an uncomplicated liberation.
For Matthew, it was more psychologically complex.
This was the world he had grown up in.
If adults repeatedly tell a young child that his body is fragile, that he cannot safely perform ordinary activities or that he requires medical equipment, the child has little independent knowledge with which to challenge those claims.
His understanding of his own body had been shaped by the adults around him.
Now that understanding had to change.
The criminal case revealed the scale of what had happened
Lisa Hayden-Johnson later admitted child cruelty and perverting the course of justice.
In January 2010, Exeter Crown Court sentenced her to three years and three months in prison.
Evidence presented around the case showed that the harm went far beyond incorrect diagnoses recorded in medical notes.
Matthew had spent a substantial part of childhood living according to restrictions associated with serious illness and disability.
Medical professionals had treated the patient they believed was in front of them.
The tragedy was that much of what they believed about that patient had been based on false information.
The story reached far beyond hospitals
The image of Matthew as an exceptionally sick child did not remain within the healthcare system.
His story attracted public sympathy.
He received a bravery award. Charitable organisations provided support and experiences for the family. He also met prominent public figures, including former British prime minister Tony Blair.
The apparent severity of Matthew’s disabilities brought the family financial and charitable assistance as well.
It would be tempting to explain the entire case through those benefits.
But human behaviour is rarely that simple.
Financial gain and public attention were documented elements of the story. Determining someone’s complete psychological motivation is another matter entirely.
That requires proper clinical assessment.
It is one reason responsible reporting should distinguish between what a court established, what individuals later said about themselves and what outsiders may infer.
Was this “Munchausen syndrome by proxy”?
That is the term many people will recognise.
“Munchausen syndrome by proxy” was historically used for situations in which a caregiver fabricated or caused illness in someone under their care, usually a child.
Modern terminology is more precise.
In the UK, healthcare and child-protection professionals commonly use Fabricated or Induced Illness (FII).
The NHS describes FII as a rare form of child abuse in which a parent or caregiver exaggerates or deliberately causes symptoms of illness in a child.
Another term readers may encounter is Factitious Disorder Imposed on Another (FDIA), which appears in psychiatric diagnostic frameworks.
They are related concepts, but they should not simply be treated as interchangeable labels.
FII is particularly useful in child safeguarding because the focus is on what is happening to the child and whether the caregiver’s behaviour is causing harm.
FDIA is a psychiatric diagnosis with specific diagnostic requirements.
That difference has practical importance: authorities do not need to establish a particular psychiatric diagnosis in a caregiver before recognising that a child is being harmed.
Fabricated illness does not always mean physically making a child sick
Popular culture tends to portray these cases in their most extreme form: a caregiver secretly poisons a child and then rushes them to hospital.
That can happen, but it is not the only pattern.
A caregiver may report symptoms that never occurred.
Real symptoms may be dramatically exaggerated.
Medical history may be misrepresented.
Samples or test results may be manipulated.
In some cases, symptoms may indeed be deliberately induced.
The common feature is that professionals are led to perceive the child’s health differently from its true state, potentially resulting in unnecessary medical intervention.
The NHS specifically recognises different ways in which illness can be fabricated or induced rather than reducing the phenomenon to a single behaviour.
What happens when a child begins to believe the diagnosis?
The physical risks are only part of the story.
Imagine experiencing childhood from Matthew’s perspective.
Adults tell you that your body cannot do certain things.
Doctors repeatedly examine you.
You take medication.
Medical equipment surrounds you.
You are transported in a wheelchair.
Food may arrive through a tube.
People praise your courage because you are supposedly fighting serious illnesses.
At a young age, there is no obvious reason to think all those adults are wrong.
The medical identity can become part of the child’s own understanding of who they are.
The NHS recognises that children affected by fabricated or induced illness may come to believe that they genuinely are ill.
Removing unnecessary treatment therefore does not necessarily undo everything that happened.
A child may also need to rediscover what their body is capable of and develop a new understanding of their own health.
When medicine unintentionally becomes part of the harm
Matthew’s case exposes an uncomfortable feature of medical abuse.
Some of the physical harm can be delivered by people who are genuinely trying to help.
A surgeon inserting a feeding tube believes there is a medical reason for doing so.
A nurse taking blood believes the test is necessary.
A doctor prescribing treatment believes there is an illness requiring treatment.
None of those actions is inherently abusive.
The problem arises when clinical decisions are based on deliberately false information.
Every medical intervention involves some balance between benefit and risk. An invasive procedure can be entirely justified when its expected benefit outweighs its dangers.
Remove the genuine medical need, however, and the equation changes.
The Royal College of Paediatrics and Child Health consequently emphasises careful assessment of the child’s actual functioning, medical history and discrepancies between what is reported and what professionals observe.
Why Matthew’s case should not make us suspicious of every persistent parent
There is an important danger in discussing stories like this.
A parent who repeatedly takes a child to doctors is not automatically fabricating illness.
Some rare diseases take years to diagnose. Symptoms can be inconsistent. Tests can initially be negative. Parents sometimes have to advocate persistently before a genuine condition is recognised.
Seeking a second opinion is not evidence of abuse.
Neither is disagreeing with a doctor.
Nor is having a child whose symptoms cannot immediately be explained.
FII is assessed through patterns and evidence, not through stereotypes about “difficult” or anxious parents.
The Royal College of Paediatrics and Child Health guidance stresses a child-centred, multidisciplinary approach when professionals encounter perplexing presentations or possible fabricated illness.
The goal is not to prove that a parent is lying.
The goal is to understand what is actually happening to the child.
In 2026, Matthew finally became the narrator of his own story
The Channel 4 documentary Love You to Death returned to the case more than 15 years after Lisa Hayden-Johnson’s conviction.
But something fundamental had changed.
Matthew was no longer the child being discussed by doctors, police officers, lawyers and journalists.
He was an adult capable of describing the experience himself.
Now 25, Matthew has spoken about learning details of his childhood that he had not fully understood before.
He has said that he does not remember feeling as sick as the medical world surrounding him suggested.
What he does remember are elements of that world: the medication, equipment and restrictions.
That distinction is striking.
A child does not need to feel seriously ill in order to believe adults who repeatedly tell him that he is.
His mother still describes the past differently
Lisa Hayden-Johnson also participated in the 2026 documentary.
Years after her conviction, she has continued to present aspects of what happened from a perspective that differs sharply from her son’s experience and from the conduct established in court.
She has defended decisions she made and maintained that she was trying to act in Matthew’s interests.
For Matthew, her response did not repair their relationship.
He has explained publicly that her attitude reinforced his decision to remain out of contact with her.
There is a broader lesson here.
A caregiver may say an action was motivated by love, fear or concern.
That does not determine whether the action harmed the child.
Intent and impact are not the same thing.
A lost childhood cannot simply be returned
It would be easy to package Matthew Johnson’s story as the tale of a deceptive mother who fooled doctors and the British public.
But that framing makes the adult the centre of the story once again.
The more important story belongs to the child.
Matthew experienced genuine medical procedures for illnesses and disabilities that, in many instances, were not genuine.
He lived with limitations created around him.
He was treated as someone whose body was far more fragile than it actually was.
And he spent formative years inside a medical identity he had not chosen.
A child can be harmed when necessary healthcare is withheld.
Matthew’s story reminds us of the opposite danger: a child can also be harmed through healthcare that was never necessary in the first place.
An unnecessary blood test still hurts.
An unnecessary medication can still produce side effects.
An unnecessary operation still leaves a wound.
And years spent believing your body cannot be trusted can matter long after the hospital equipment disappears.
Matthew is now an adult with the ability to define himself beyond the patient he was once believed to be.
What cannot be restored are the years in which other people defined his body for him.
Perhaps that is the most important lesson left by his case.
Protecting children does not only mean making sure they receive the medical care they need. It also means protecting them from medical care they never needed at all.
Sources and further reading
This article draws on contemporary reporting about the criminal case, later reporting surrounding the 2026 documentary, and UK medical guidance on Fabricated or Induced Illness.
The Guardian – Mother jailed for faking son’s illness
The Guardian – Love You to Death review
BBC – Childhood ‘taken from me’ through fake illnesses
NHS – Fabricated or induced illness
Editorial note: This article discusses a documented child-abuse case alongside general medical information about FII and FDIA. It does not attempt to retrospectively diagnose Lisa Hayden-Johnson with a psychiatric disorder. Court-established facts, personal accounts and general medical information have been treated separately.